
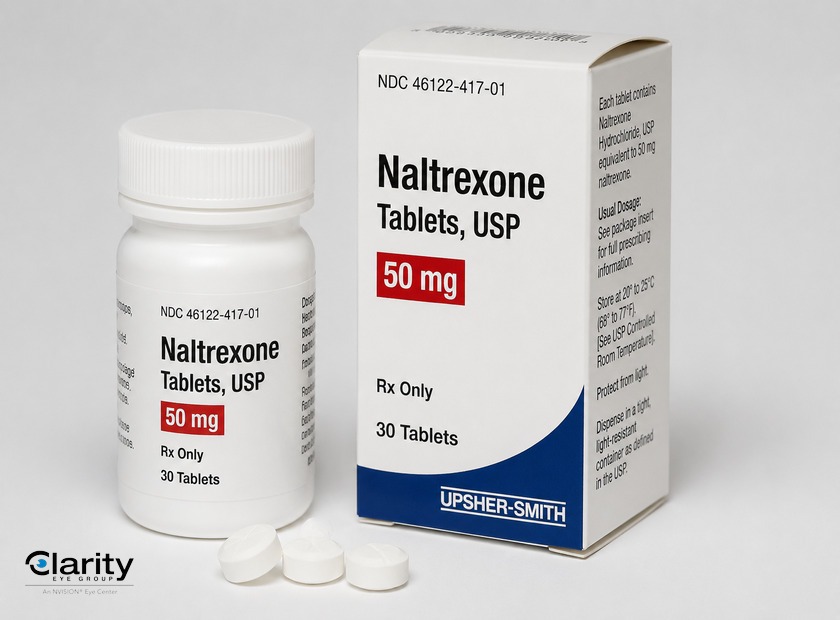
Buy naltrexone online for alcohol and opioid dependence — a daily 50 mg tablet that blocks opioid receptors and takes the reward out of a drink. A tenth of that dose is a different medicine altogether, taken for pain and inflammation. The label never mentions that second use. It exists only as a pharmacy preparation, made to order.
| Name | Strength | Starting Price |
|---|---|---|
| Naltrexone tablet (generic ReVia) | 50 mg | From $1.14 per tablet |
| Extended-release injection | 380 mg | From $1,716.48 per vial |
| Compounded low dose | 1.5 mg · 3 mg · 4.5 mg | No published price |
Tablet and injection figures are federal benchmark prices for the week of 19 August 2026. A benchmark is what pharmacies pay, not what a counter charges. The third row is explained further down.
What this page covers
Naltrexone Is an Opioid Blocker Used for Two Conditions
Naltrexone is a prescription tablet that occupies opioid receptors and holds them closed. Two uses carry an approval in adults. One is alcohol dependence, and the other is blocking opioid effects after detoxification.
It is not an opioid, and it delivers nothing of its own. No pain relief, no sedation, no lift in mood. People who expect to feel the first tablet are usually disappointed. That absence is the point of the treatment.
The active ingredient is naltrexone hydrochloride. The tablet reached American pharmacies as ReVia and as Depade. Both brand names have largely left retail. Generic naltrexone is what a pharmacy stocks today. The same molecule also exists as a monthly injection, and it forms one half of an approved weight tablet. Both appear further down.
The gap between those two doses is wider than the gap between many separate medications. One is a full blockade taken every day. The other is a tenth of it, taken for something the label never mentions. Adults who buy naltrexone online are choosing between those two rather than between two products.
Two approved conditions is the whole of the label. Most of the interest in it sits outside those two. Weight, pain, autoimmune disease. That line between approved and merely used runs through this page.
How Naltrexone Works and Why It Is Not an Opioid
How naltrexone works is unusually simple to describe. It binds the mu-opioid receptor and switches nothing on. An opioid arriving afterwards finds the seat taken and produces no effect.
The prescribing information calls that binding competitive, and the word carries a warning inside it. Competitive means surmountable. Enough opioid will eventually push past the blockade, and people who try are the ones who die.
Naloxone is the other antagonist people meet, and the two get confused constantly. Naloxone reverses an overdose in minutes and fades within the hour. Naltrexone holds receptors for a day and is useless in an emergency. Neither one is an opioid, and neither can be swapped for the other.
One Naltrexone Strength and Three Dosing Intervals
Exactly one oral strength is made in the United States, and it is a scored 50 mg film-coated tablet. The federal registry of marketed products lists forty-five finished tablet entries. Every one is 50 mg.
So naltrexone dosage adjusts the calendar rather than the tablet. The label describes three supervised schedules, and each one buys a predictable length of blockade.
| Amount taken | Tablets | Blockade lasts | Typical pattern |
|---|---|---|---|
| 50 mg | One | About 24 hours | Every day |
| 100 mg | Two | About 48 hours | Every other day |
| 150 mg | Three | About 72 hours | Every third day |
Durations as stated in the prescribing information. Longer intervals reduce the depth of the blockade, and the label says so plainly.
Those larger amounts exist for supervised dosing, not for convenience at home. The label attaches a caution to them, since single doses above 50 mg carry a higher risk of liver injury. That caution has its own section at the end of this page.
Timing inside the day matters less than people expect, though anyone who feels queasy on it usually moves the tablet to the evening. The first tablet works within hours. There is no loading period. Absorption is nearly complete, and peak levels of the parent and its metabolite both arrive within an hour.
Two numbers explain why the blockade outlasts the chemistry. The naltrexone half life is roughly four hours. Its active metabolite, 6-beta-naltrexol, runs about thirteen. How long naltrexone stays in your system is one question. How long it holds a receptor is another, and the receptor answer is always the longer one.
Naltrexone for Alcohol Dependence and Opioid Blockade
Naltrexone for alcohol does not stop anyone from drinking, and it was never designed to. It removes the payoff, so heavy drinking becomes less rewarding and relapse becomes less likely.
This is worth separating from the older approach it gets grouped with. Naltrexone and alcohol together produce no flushing, no vomiting and no punishment. Nothing dramatic happens. The drink lands flatter than memory promised, and over weeks that dulling does the work.
The naltrexone dose for alcohol is the ordinary one: 50 mg daily. Guidelines for alcohol use disorder list it alongside a few other options, and choosing between them belongs in an appointment.
Drinking on naltrexone raises a second question with a harder answer. Alcohol still reaches the liver at exactly the same rate. Blunted reward is not reduced harm, and nothing about the tablet protects an organ.
One protocol uses the tablet differently. A tablet goes down an hour before drinking. Nothing is taken on dry days. That approach carries the name of the researcher behind it, and it remains argued over rather than settled.
The second approval is narrower than the first and far less forgiving. It covers people who have already completed opioid detoxification, and starting too early precipitates withdrawal within minutes. The label sets a minimum opioid-free interval of seven to ten days for short-acting opioids. Anyone coming off buprenorphine or methadone can stay vulnerable for as long as two weeks. A naloxone challenge test exists for cases where waiting is not enough.
Four situations rule out a start entirely:
- Current use of any opioid, including tramadol and prescribed pain medication
- Acute opioid withdrawal already underway
- A positive urine screen for opioids, or a failed naloxone challenge
- Known sensitivity to the molecule or to anything else in the tablet
Buy Naltrexone Online With a Prescription in Hand
To buy naltrexone online you need a prescription first, in all fifty states, without exception. Pharmacies that ship naltrexone online hold the same licenses as the one on the corner.
A naltrexone prescription online is straightforward for one specific reason. The molecule carries no controlled substance schedule, so none of the federal rules on remote prescribing apply to it. A video appointment is usually enough, though individual state rules on telemedicine still apply.
Naltrexone over the counter does not exist, and scheduling has nothing to do with why. The barrier is the seven-to-ten-day opioid-free window described above. A tablet taken a few days early throws someone into withdrawal, and no shelf can check that history.
That history is most of the appointment. Expect questions about every opioid taken in the last fortnight. Cough syrup and post-surgical leftovers count. Expect the start date to move by a week when the answers are unclear. Liver enzymes are usually checked at some point. The label does not demand them before a first tablet.
One quirk shows up at the pharmacy counter rather than in the appointment. The manufacturer on the bottle changes between refills more often than with most generics, because two suppliers left the market recently. The four that remain package differently. Inside is the same tablet. Only the bottle and the count change.
What Naltrexone Costs Against One Monthly Shot
Naltrexone cost without insurance is the version people actually ask about, and the tablet answers it kindly. Thirty tablets sit near thirty-four dollars at the federal benchmark, and a pharmacy that publishes its own formula charges under twenty-three. Where to buy naltrexone online matters less than which of those two numbers a pharmacy started from.
| Quantity of 50 mg tablets | Federal benchmark | Published pharmacy price |
|---|---|---|
| 30 tablets — one month | $34.18 | $22.94 plus $5 shipping |
| 60 tablets — two months | $68.35 | Offered |
| 90 tablets — three months | $102.53 | Offered |
| One 380 mg injection — one month | $1,716.48 | Not sold this way |
Benchmark figures from the National Average Acquisition Cost file, week effective 19 August 2026. Pharmacy figure published by Cost Plus and read on 29 August 2026. Their own retail reference is $102.00 for the same thirty tablets.
Read the last row twice. Fifty times the tablet price buys the same molecule for the same month. Needle instead of mouth. That is the real comparison behind a monthly injection against a daily tablet, and the injection still has reasons to exist. Nobody forgets a shot.
Counting a supply is where the arithmetic goes sideways. One supplier bottles by sixty. Another blisters by thirty. A ninety-day fill can arrive as three packs or as one and a half. Ask for the count rather than the month.
Both figures moved during 2026, and they moved in opposite directions. The tablet benchmark fell from $1.26432 in January to $1.13919 in August. Four steps down with no rebound. The injection rose by nearly six percent across the same months. Discount card programs quote lower numbers still. A naltrexone coupon changes with the pharmacy and the postal code, so none of those figures belong in a table.
One row has no number at all. Low dose naltrexone cost cannot be quoted from any benchmark, because compounded preparations never enter one.
Naltrexone Weight Loss Runs Through Food Reward
Naltrexone for weight loss is not an approved use on its own, and searches on the phrase mostly return a combination product. The molecule does have a place in weight medicine. It just does not hold that place alone.
The mechanism explains why. Mu-opioid receptors sit in the reward pathway as well as the pain pathway, and palatable food activates them. Block those receptors and the pull of specific foods weakens before general hunger does. People describe wanting the second helping less rather than feeling full sooner.
That distinction predicts who notices anything. Someone who eats past fullness because the food is good may notice a change in weeks. Someone whose problem is portion size at a normal meal often feels nothing at all.
Timing questions come up constantly here and have a dull answer. Morning dosing is conventional and evening dosing is common, and no trial has shown one to beat the other. Consistency is worth more than the hour.
Compounding pharmacies sell a three-part capsule that pairs the molecule with topiramate and vitamin B12. The B12 rides along for energy claims rather than for fat, and the trio has never been tested as a unit. That capsule is prepared to order, and it has never been through an approval process as a finished product.
A newer question comes from people already on a GLP-1 medication. Can this be added? Pharmacologically the two do not collide, since one works on gut hormones and the other on reward. Whether stacking them adds anything is unstudied. Any serious plan for medical weight management starts by picking one mechanism deliberately.
Bupropion Added to Naltrexone in One Tablet
The approved product pairs 8 mg of the blocker with 90 mg of bupropion in an extended-release tablet. Naltrexone and bupropion do different halves of one job.
Bupropion stimulates the neurons that signal satiety. Those same neurons then release a substance that switches them off, and the blocker removes that brake. One half presses the accelerator. The other cuts the feedback loop. Neither ingredient does much for weight alone.
Trial results are modest and honest. Across the registration program the combination beat placebo by roughly four to five percent of body weight over a year. Diet and activity ran alongside it. Real-world cohorts land in the same neighbourhood. Nausea is the reaction that ends treatment most often, and it does so early.
Some people assemble the pair from two separate generic tablets, and the search volume behind that idea is substantial. The doses do not match the approved product, the release profile differs, and the titration schedule that made it tolerable disappears.
Low Dose Naltrexone Has No Tablet of Its Own
Low dose naltrexone means 1.5 mg to 4.5 mg a day, roughly a tenth of the approved amount. No manufacturer makes a product at those strengths, and that is not an oversight.
The federal registry makes the situation unusually clear. Every finished oral entry is the 50 mg tablet. The low strengths appear instead as raw powder. Sixty-eight entries are bulk ingredient rather than a finished product, and twenty-seven of those are registered specifically for prescription compounding.
So a 4.5 mg capsule is made to order under section 503A, on a prescription that names one person. Its safety and effectiveness in that form have never been evaluated. This is also why it has no benchmark price and no discount card. No chain pharmacy shelf either.
Dosing climbs slowly by convention rather than by label. A common schedule starts at 1.5 mg for a week, then adds another 1.5 mg each week until 4.5 mg. Evening dosing is usual and deliberate, because the rebound this treatment depends on is thought to arrive overnight.
That rebound is the whole idea. A small amount blocks receptors briefly, and the body answers by raising its own opioid signalling. That increase outlasts the blockade. A second and better-documented action runs alongside it. The molecule dampens a receptor called TLR4 on glial cells, and inflammatory signalling in the nervous system falls with it. Nothing like that happens at 50 mg.
Two practical questions dominate the forums. Taking a little too much of the low dose is not an overdose. Reports describe a night of vivid dreams and a headache. The fix is dropping back a step. Stopping is equally undramatic, because there is no dependence and no taper written anywhere. Symptoms that the treatment was holding down tend to return over a few weeks.
What to Avoid While Taking Low Dose Naltrexone
Opioids top the list at any dose. The list is longer than most people assume. It includes tramadol, codeine in cough preparations and anything left over from a surgery.
The items that catch people out are the ones sold without a prescription:
- Loperamide for diarrhea, which acts on the same receptor family in the gut
- Dextromethorphan, the active ingredient in most cough syrups
- Kratom, which behaves as an opioid whatever the packaging says
- Immunosuppressive treatment after a transplant, where an immune-modulating effect works against the point
One more item belongs on this list even though it harms nobody. A urine screen can read positive for opiates during treatment, and telling the laboratory beforehand saves an afternoon. Naltrexone interactions beyond this group are few, and the tablet leaves most prescriptions alone. Stimulants are a common worry and a needless one, since naltrexone and Adderall act on unrelated systems.
Long term side effects of the low dose are a separate question. Low dose naltrexone side effects look nothing like those of the full tablet. Vivid dreams are the complaint reported again and again. Sometimes pleasant, sometimes not. They usually settle within a fortnight.
Beyond that the honest answer is thin. Trials have run for weeks and months rather than years, so long term data on this dose barely exists. The parent molecule does carry four decades of use at ten times the amount.
Insomnia is why people move the capsule earlier in the evening, and that works often enough to try first. Headache and mild nausea show up in the first week and rarely outlast it.
Pain and Inflammation Trials Behind the 4.5 mg Dose
Naltrexone for pain has real trial evidence in some conditions. In others it has only patient reports. Sorting those two piles is the useful part.
Fibromyalgia is where the evidence is strongest. A crossover trial summarised in a review of the therapeutic literature found about a third of participants responding. On placebo it was roughly one in nine. The numbers are small and the trials are short. They are still trials.
Crohn’s disease has its own blinded work, with endoscopic improvement reported alongside symptom scores. Few off-label uses come with something visible to measure. Multiple sclerosis has trials pointing at quality of life rather than at disease progression.
Naltrexone for inflammation as a general claim goes further than the data does. The TLR4 mechanism is plausible and partly documented. For most conditions plausible is where it stops. Naltrexone for anxiety belongs in that group, resting on reports rather than on any controlled work.
Hashimoto’s thyroiditis is the clearest example of the second pile. Clinicians report falling antibody titres and better symptom scores. No trial has tested it directly. Anyone weighing it as part of thyroid care deserves that gap stated out loud. Naltrexone for chronic pain in general sits between the two piles, closer to the first.
Which Naltrexone Side Effects Come From the Block?
Most of them do. The body runs its own opioid signalling all day. Removing it produces a recognizable cluster. Nausea, headache, restlessness, broken sleep, low energy.
Reading them that way explains their timing. They arrive in the first days and fade as the system adjusts, so the first week is worth pushing through.
| Reaction | Rate in trials | Comes from the blockade |
|---|---|---|
| Nausea | 10% | Yes |
| Headache | 7% | Yes |
| Dizziness | 4% | Yes |
| Fatigue | 4% | Yes |
| Insomnia | 3% | Yes |
| Anxiety | 2% | Yes |
| Somnolence | 2% | Yes |
| Injection site reactions | Injectable form only | No — the carrier not the block |
New-onset reaction rates in the alcohol dependence trials, from the prescribing information. The final row belongs to the injectable form.
Nausea deserves the attention it gets, because it ends more courses than anything else. Taking the tablet with a meal blunts it, and so does starting at half a tablet where a prescriber agrees.
Does naltrexone make you sleepy is asked often. Somnolence reaches two percent in those same trials, and insomnia is the more common complaint at three. Fatigue does appear in trials, and it travels with poor sleep rather than with any sedative effect.
One risk sits apart from the rest. Blocking receptors for weeks lowers opioid tolerance, so a dose that was survivable before treatment can be fatal after it stops. The danger peaks in the days after a missed refill or a decision to quit. Nothing else about ending this medication matters more.
Naltrexone Narrows the Pupil for Reasons Unknown
Naltrexone produces some pupillary constriction, and the prescribing information adds that the mechanism is unknown. That is an unusual sentence to find in a label. Opioids narrow the pupil, so the medication built to block them was expected to do nothing of the kind.
The opposite happens when the timing is wrong. Given to someone still carrying opioids, naltrexone strips the receptors within minutes and precipitates withdrawal. Wide pupils and streaming eyes are among the first signs anyone notices. That is why the label asks for an opioid-free interval after short-acting opioids. Seven to ten days is the minimum. People coming off buprenorphine or methadone stay vulnerable for as long as two weeks. A naloxone challenge settles the question where doubt remains.
For an eye examination the practical point is small and worth knowing. A pupil that does not match the room has a short list of causes. This tablet belongs on it in either direction. Anyone bringing an unexplained pupil finding to a clinic should have naltrexone on the medication list. Leaving it off as unrelated to the eye is the common mistake.
The same receptor family sits in the cornea. That is why this molecule has a line of eye research of its own. A group at Penn State worked on it for two decades. Topical naltrexone restored re-epithelialisation in diabetic rats, and a later study found it worked independently of insulin without adding to it. Delayed epithelial healing and recurrent erosions are genuine and under-recognized complications of diabetes in the cornea. They sit alongside the retinal changes that bring most people to a diabetic eye examination.
None of that describes the tablet. It was a drop, given to animals, and no approved ocular product came out of it. The reason it belongs here is narrower: it explains why an opioid blocker keeps turning up in ophthalmology at all.
The Liver Warning the FDA Removed in 2013
This tablet carried a boxed warning about liver toxicity for decades, and it does not carry one now. FDA issued the safety labeling change notice on 26 July 2013 and approved the revised label later that year. The injectable form lost the same warning.
The original alarm came from studies in the 1980s that used up to 300 mg a day. That is six times the approved amount. At those doses liver enzymes rose. At 50 mg no pattern of liver failure caused by the tablet ever emerged. Where transaminases did climb the label points at other causes first, from hepatitis B and C to alcohol-related liver disease.
Removing a box is not removing a caution. Hepatotoxicity keeps its own heading under precautions. The label still flags anything above a single 50 mg dose. Enzyme checks remain reasonable for a liver already under strain. What changed is the weight of the claim, and much of the writing on this medication has not caught up.
Two related questions follow it around. Naltrexone is not a controlled substance and appears on no DEA schedule. It is not addictive either. There is no reward in it to chase. The two questions arrive together for one reason. People assume anything used in addiction treatment must itself be controlled.
Naltrexone contraindications stay narrow: current opioid use, acute withdrawal, and known sensitivity. Pregnancy is not an absolute barrier, and experience there remains limited, so it stays a conversation rather than a rule.
Medical Disclaimer
This page is educational and does not replace individual medical care. Naltrexone requires a prescription in the United States, and starting it while opioids remain in the body can cause sudden withdrawal. Compounded low doses are prepared by pharmacies and have not been evaluated as finished products. Talk to your doctor or pharmacist before starting, stopping or changing any treatment. Seek care the same day if abdominal pain, dark urine or yellowing of the skin appears.