
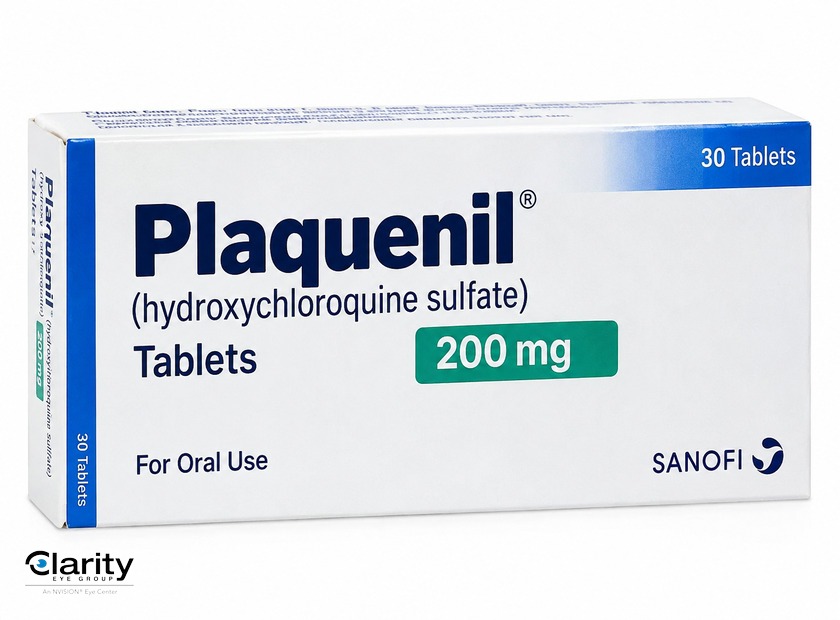
Buy Plaquenil online — 200 mg hydroxychloroquine for lupus and rheumatoid arthritis, taken for years and tied to a yearly eye exam you cannot skip. That length is the whole reason an eye clinic gets involved at all. The retina quietly absorbs the exposure that builds up along the way. Screening built around that problem changed in 2025.
| Name | Strength | Starting Price |
|---|---|---|
| Plaquenil (hydroxychloroquine sulfate) | 200 mg tablet · one strength only | From $0.12 per tablet |
One tablet strength is manufactured. Every daily amount is built from it.
What this page covers
What Plaquenil Is and Which Conditions It Treats
Plaquenil is hydroxychloroquine sulfate. The approved labeling covers four things. Rheumatoid arthritis in adults. Systemic lupus erythematosus in adults. Chronic discoid lupus. And malaria, both treatment and prevention, in areas where chloroquine still works.
The malaria heritage explains the rest. It began as an antimalarial and turned out to calm autoimmune disease on the side. That second career is now the reason almost everyone takes it. Lupus and rheumatoid arthritis together account for the overwhelming majority of prescriptions written in the United States. People who buy Plaquenil online are almost always in one of those two groups.
What it does inside a cell is less tidy than a modern biologic, and the labeling admits as much. It records that the mechanisms behind the anti-inflammatory and immunomodulatory effects are not fully known. What follows is the leading explanation rather than a settled one. It raises the pH inside lysosomes. It interferes with how immune cells present pieces of protein to one another. And it damps down signalling through several toll-like receptors. The effect is broad rather than targeted. That breadth is why it helps in conditions as different as lupus, Sjögren’s and rheumatoid arthritis. It is also why nobody can say which of those actions matters most.
Two uses sit outside the label and turn up constantly in conversation. Sjögren’s syndrome is one, where it is prescribed for joint pain and fatigue rather than for dryness. Fibromyalgia is the other. The evidence there is thin, and most rheumatologists treat it as a trial rather than a plan.
Methotrexate comes up alongside it more often than any other name. The two are not interchangeable. Methotrexate is stronger, works faster and asks for blood tests every few months. Hydroxychloroquine is milder and slower, and its monitoring is lighter rather than absent. The label asks for blood counts periodically on prolonged treatment. In rheumatoid arthritis the two are often combined rather than compared. In lupus hydroxychloroquine is the backbone that nearly everybody stays on.
Is Plaquenil an Immunosuppressant or a Steroid?
Neither label fits cleanly, and that is the honest answer. It is not a steroid. It contains no cortisone, it does not thin bone, and stopping it does not require a taper.
Immunosuppressant is closer but still loose. Rheumatologists usually call it an immunomodulator. It adjusts immune signalling rather than shutting a limb of the immune system down. The practical difference shows in infection risk. Methotrexate and biologics raise it measurably. Hydroxychloroquine largely does not. That is why it is the one antirheumatic that often continues through surgery, pregnancy and infection.
Pregnancy is the clearest case. Hydroxychloroquine is generally continued rather than stopped. Uncontrolled lupus is more dangerous to a pregnancy than the tablet is, and stopping tends to bring a flare at the worst possible moment. Surgery follows the same logic. Most operations need no pause at all, which separates it sharply from methotrexate and from the biologics.
It belongs formally to the disease-modifying antirheumatic medications, the group written DMARD on a clinic letter. Within that group it sits at the gentle end. It is also not a blood thinner. It is associated with less clotting in antiphospholipid syndrome, and that is where the confusion comes from, though the label does not approve it for that.
How Long Plaquenil Takes to Work and When to Take It
Weeks to months, and the label says so in those words. The action is cumulative rather than immediate. Most people notice nothing at all in the first month and something real between months two and four.
The pharmacology explains the wait. The terminal half-life runs 40 to 50 days. The medicine is also distributed extensively into tissue, far above its blood level. At that rate blood levels keep climbing for months after the first tablet. Nothing you do speeds it up.
That slowness cuts both ways and is worth knowing before month two. Stopping for a fortnight changes almost nothing. The reservoir empties as slowly as it filled. A flare three weeks after a missed run of tablets is usually not withdrawal. It is the disease.
Stopping altogether follows the same clock and the question comes up often. There is no withdrawal syndrome and no taper. What returns is the disease itself, and it returns slowly rather than at once, because tissue levels fall over months. People who stop frequently feel fine for a good while. Then the joint pain and the fatigue creep back. That delay is exactly what makes an unplanned stop hard to connect to the flare that follows it.
Timing within the day is a comfort question rather than an efficacy one. Nausea is the most common early complaint. Taking the tablet with food blunts it. Many people move it to the evening for that reason. That is where the habit of taking it at night comes from. Split it into two doses if a single 400 mg amount sits badly. None of these choices changes how well it works.
Plaquenil Dosage by Weight and the 400 mg Ceiling
One number governs the whole prescription. The label states it plainly. Daily doses above 5 mg per kilogram of actual body weight increase the incidence of retinopathy. Not ideal weight. Not lean weight. Actual weight, as measured on the day.
Only a 200 mg tablet exists, so the daily amount is assembled from halves and wholes. That arithmetic decides more than it looks.
| Body weight | Ceiling at 5 mg/kg | Nearest tablet amount |
|---|---|---|
| 50 kg · 110 lb | 250 mg | 200 mg daily |
| 60 kg · 132 lb | 300 mg | 200 mg daily or alternating 200 and 400 |
| 70 kg · 154 lb | 350 mg | alternating 200 and 400 mg |
| 80 kg · 176 lb and above | 400 mg | 400 mg daily |
Ceilings follow the 5 mg/kg limit in the approved labeling. The final amount is a prescriber decision.
Read the bottom row carefully, because it is where the ceiling stops rising. Above roughly 80 kg the calculation would allow more than 400 mg. Practice holds at 400 mg anyway. A heavier person does not get a proportionally larger dose. Weight sets the ceiling for people below that line, not a target for people above it.
Approved amounts differ slightly by condition. Rheumatoid arthritis starts at 400 to 600 mg daily. It settles to 200 to 400 mg for the long run. Lupus, both systemic and discoid, is 200 mg once daily or 400 mg as one dose or two. The lowest amount anyone takes routinely is 200 mg, which is a single tablet.
Buy Plaquenil Online or Fill Generic Hydroxychloroquine
You can buy Plaquenil online in the United States only against a prescription. For a medication taken this long that is rarely the obstacle. The prescription usually already exists. The real choice is between the brand name and the generic. And whether to fill three months at a time.
Generic hydroxychloroquine sulfate is the same molecule at the same 200 mg strength. Nearly every pharmacy stocks it. Nearly every plan pays for it. The brand is not better made. It is older, and its price reflects a name rather than a difference in the tablet.
A small thing catches people out at the counter. The manufacturer on the bottle changes between refills more often than with most generics. The tablet may arrive a different shape or shade. That is a change of supplier and not a change of medication. What matters is the strength printed on the label.
Anyone ordering Plaquenil online for the first time should bring three things. The current daily amount. The date treatment started. And the date of the last eye examination. That third item is the one nobody expects and the one a careful prescriber asks for.
What Plaquenil Costs With and Without Insurance
This is one of the cheapest long-term medications in American pharmacies. The published numbers are worth reading before accepting a copay. The federal benchmark for what a pharmacy pays sits under fifteen cents a tablet. Retail asks more than sixteen times that.
| Pack of 200 mg tablets | Published retail | Cash price | Per tablet |
|---|---|---|---|
| 30 tablets · one month at 200 mg | $73.20 | $6.97 | $0.23 |
| 60 tablets · one month at 400 mg | $146.40 | $8.93 | $0.15 |
| 90 tablets · three months at 200 mg | $219.60 | $10.90 | $0.12 |
| Pharmacy acquisition cost | — | $4.46 per 30 | $0.14854 |
Retail comparisons and cash prices are published by Mark Cuban Cost Plus and were read on 31 August 2026. The acquisition figure is the CMS National Average Acquisition Cost, effective 19 August 2026. Shipping is added at checkout.
Compare the first and third rows properly. Ninety tablets cost less than four dollars more than thirty. The dispensing work is charged once per fill rather than once per tablet. That pharmacy publishes the breakdown. It is $1.71 for the medicine itself, twenty-six cents of markup and five dollars of pharmacy labour. On a tablet taken for a decade, quarterly filling is the largest saving available.
A Plaquenil 200mg price of twenty-three cents a tablet also changes how insurance reads. A routine generic copay runs ten or fifteen dollars. That sits above the cash price for the identical tablet, so the covered route can be the more expensive one. Checking both takes a minute.
Discount cards work here. The saving is smaller than the advertising suggests, because they cut a retail figure that was inflated to begin with. A Plaquenil coupon cannot be combined with insurance on the same fill. You pick one and the pharmacist runs whichever you name. Brand Plaquenil has no entry in the federal acquisition file at all. That tells you how rarely it is dispensed now.
Plaquenil Side Effects in the First Three Months
Most Plaquenil side effects belong to the stomach and to the first weeks. Nausea leads. It eases when the tablet moves to a meal. Loose stools, cramping and a poor appetite fill out the same group and fade on the same timetable.
Headache and a light-headed hour after the dose turn up next, and both usually settle by the second month. Fatigue is reported often and interpreted badly. Lupus and rheumatoid arthritis produce fatigue of their own. Moving the dose to bedtime sorts out which is which. That beats guessing.
Alcohol has no direct interaction here and the label sets no limit. The caution that circulates comes from the company this tablet keeps. Methotrexate taken alongside is the medicine with the liver concern, and the advice belongs to that rather than to this one.
Three reactions sit outside that ordinary group and belong to the label’s warnings rather than to its nuisance list. Serious skin reactions including Stevens-Johnson syndrome and toxic epidermal necrolysis are recorded. A rash that blisters or peels is a same-day matter rather than a wait. Cardiomyopathy and ventricular arrhythmia appear as rare but potentially fatal events. Hypoglycemia is described on the label as severe and potentially life-threatening, and it occurs with or without any diabetes medication in the picture. Unexplained shakiness or confusion is worth acting on rather than dismissing.
Hair Skin Sun and What Plaquenil Does to Teeth
Hair thinning is reported and it is usually modest and reversible. It arrives as a general thinning rather than patches. It recovers after stopping. Telling it apart from the hair loss lupus itself causes is harder. The timing usually settles it.
Skin gets two distinct effects. The first is sun sensitivity. It is real enough that daily sunscreen belongs in the plan from the start rather than after the first burn. The second is pigmentation. It is the one people find alarming, because nobody warned them. Blue-grey or slate patches can appear after years of treatment. The shins, the face, the roof of the mouth and the gums are the usual sites.
That mouth pigmentation is what sits behind the questions about Plaquenil and teeth. The teeth themselves are not stained. What changes is the gum and the hard palate behind them. The discolouration sits in the tissue rather than on the enamel. It fades slowly after stopping and often incompletely. A dentist who has not seen it before may mistake it for something else. Name it at the appointment.
Does Plaquenil Cause Weight Gain?
Weight gain is not a listed effect of hydroxychloroquine, and the controlled data do not support it. Appetite loss appears on the label rather than appetite increase. Most reported gain has simpler explanations than the tablet.
Two of them account for nearly all of it. Steroids are frequently taken alongside, especially early, and prednisone does drive weight up. And a disease finally under control lets eating and living return to normal. That shows on a scale as gain even though it represents recovery.
Weight loss gets asked about too, usually hopefully. There is no evidence it produces any, and no approval anywhere covers it. Where the number moves early, nausea is the likeliest reason. It is not a result worth keeping.
The Retina Is the Reason This Tablet Gets Watched
Most of what stands above can be managed, adjusted or waited out. This cannot. The label’s own words are that irreversible retinal damage was observed in some patients. It relates to cumulative dose and treatment duration. Irreversible is the word that organizes the rest of this page.
The mechanism is a slow accumulation rather than a reaction. Hydroxychloroquine binds to melanin and gathers in the pigmented layer beneath the retina. It stays there for months after a course ends. Photoreceptors sitting on that layer are damaged gradually. They do not regenerate. Nothing about this happens quickly, which is precisely the problem.
A 2026 review of prevention and detection makes the same point. Risk tracks total exposure rather than any single tablet. Below five years of treatment at a correct dose the risk is small. It climbs with years of use. It climbs faster where the daily amount runs above the weight-based ceiling. This is the reason the weight calculation further up exists at all.
One detail separates this from most medication side effects and it deserves stating plainly. Retinal changes and visual disturbances can continue progressing after the medication stops. Catching it early does not undo what has happened. It limits how far it goes.
What a Plaquenil Eye Exam Actually Involves
It is not the examination you get for glasses. A Plaquenil eye exam is a retinal screening built around imaging. Reading a letter chart is the smallest part of it. Expect dilating drops and a longer appointment than a sight test.
Four things happen, and each answers a different question:
- Best corrected visual acuity. How well each eye reads with the right lenses in front of it. This is the baseline everything else is compared against.
- Optical coherence tomography. A cross-section of the retina layer by layer. Thinning in a specific layer shows here before anyone notices anything.
- Fundus autofluorescence. A wide photograph that makes damaged pigment glow differently from healthy pigment. It covers ground beyond the macula that a narrow test misses.
- A visual field test. Pressing a button when small lights appear. It maps function rather than structure and confirms what the images suggest.
None of it hurts and none of it involves a needle. The dilating drops blur near vision for several hours. Somebody else should drive home, and sunglasses are worth bringing.
Cost is the question people ask and rarely find answered. In the United States this is a medical examination rather than a vision one. It is coded against the diagnosis of long-term medication use rather than billed to a glasses benefit. What you pay therefore depends on your medical plan and not on your vision one, and the two are often different policies.
What comes back is a comparison rather than a verdict. This year’s images are read against last year’s, which is why the baseline matters and why switching clinics mid-course is awkward. Ask for a copy of the scans and not only the letter.
Two things are worth settling before the first visit. Searching for a Plaquenil eye exam near you is only half the job, because the practice needs optical coherence tomography and wide-field imaging on site and a routine sight test includes neither. And name the medication and the number of years on it when booking a screening appointment, because that decides what gets scheduled and how long the slot needs to be.
Why OCT and Autofluorescence Now Come First
The order of those tests changed, and most of what is written online has not caught up. Imaging is now the primary screening tool and the visual field has become a confirmatory one. That reverses how screening was described for the previous decade.
The reasoning is about what fails first. Structural damage on optical coherence tomography and pigment change on autofluorescence appear early. They show before a person can report anything, and before a field test reliably finds a defect. Fields depend on attention, fatigue and practice. A first abnormal result often needs repeating. An image does not have an off day.
Wide-pattern autofluorescence earns its new place for a second reason. Toxicity does not always begin in the same spot. Most eyes of European heritage show a parafoveal pattern, a ring just outside the center. Eyes of East Asian heritage more often show a pericentral pattern further out. A test aimed only at the central ten degrees can miss it entirely. A wide image looks at both without having to choose.
New Plaquenil Screening Guidelines After 2025
The American Academy of Ophthalmology revised its screening recommendations in 2025, a decade after the previous version. The schedule below is what came out of it.
| When | What is done | Why |
|---|---|---|
| Soon after starting | Fundus examination with OCT and autofluorescence | Rules out existing disease and sets the comparison |
| Years one to five · no risk factors | Screening may be deferred | Toxicity below five years at a correct dose is uncommon |
| Years one to five · with risk factors | Annual OCT and autofluorescence | Risk arrives earlier in this group |
| After five years · everyone | Annual OCT and autofluorescence | Cumulative exposure is now the driver |
Schedule follows the 2025 revision of the ophthalmic screening recommendations. Fields and multifocal electroretinography are used to confirm rather than to screen.
Two changes matter more than the rest. The baseline examination moved earlier, from within the first year to soon after starting. Its value is as a comparison, and a comparison taken late is worth less. And the deferral in the first five years is now conditional. It applies only where there are no significant risk factors.
A newer field algorithm called 24-2C also appears in the revision. It samples the parafoveal and pericentral regions in one test. That removes the old need to choose a pattern based on ancestry. It remains a confirmatory test rather than a screening one.
One thing the revision declines to endorse is worth reporting honestly. Artificial intelligence analysis and several newer imaging methods have been studied. None is validated for general screening or widely available. Offered as a substitute for the standard tests, they are something the guidance does not yet support.
Who Carries More Risk Than the Dose Suggests
Dose and duration set the baseline. Four other things move a person above it. Three of them sit on the label and the fourth arrived in 2025.
- Reduced kidney function. Hydroxychloroquine is cleared partly by the kidneys, so impairment raises the level reached at any given dose.
- Tamoxifen taken alongside. Named on both the label and the ophthalmic guidance, and a common combination in women treated for breast cancer.
- Existing disease at the macula. A retina already altered is harder to read and starts from less reserve.
- Starting treatment at an older age. Added in the 2025 revision and absent from older advice entirely.
The first three have been on the list for years. The fourth is new, and it changes who gets screened early rather than deferred. Somebody beginning treatment in their seventies is no longer in the same category as somebody beginning in their thirties. The identical dose does not make them equal.
None of this is a reason to stop a medication that is working. It is a reason to know whether any of those four applies to you before five years pass. The deferral only holds if none of them does.
Early Plaquenil Retinopathy Has No Symptoms
This is the sentence the whole page exists for. Early hydroxychloroquine retinopathy produces nothing a person can feel. Vision stays sharp, the letter chart stays normal, colors look right. The damage is found on an image or not at all.
By the time symptoms appear the picture has usually moved on. What people describe then is difficulty reading despite clear distance vision. Letters drop out of the middle of a word. A ring of dimness shows up, easier to notice at night. Those are late findings rather than early warnings.
The classic bull’s-eye appearance belongs later still. It is a ring of damage circling a preserved center, visible on examination. By then a meaningful amount of retina has gone. Screening exists specifically to find the problem several years before anything looks like that.
What happens after detection depends on how far it went. Mild retinopathy is unlikely to progress once the medication stops. Severe retinopathy may continue worsening for years afterwards, which is the strongest argument for finding it early. The decision to stop, reduce or continue with closer monitoring belongs to the prescriber and the ophthalmologist together. Increasingly it is a conversation rather than an automatic withdrawal.
If you have been taking this tablet for years and cannot remember your last retinal screening, that is the finding. An examination arranged now settles a question that no symptom will answer for you.
Medical Disclaimer
This page is educational and does not replace individual medical care. Hydroxychloroquine requires a prescription in the United States. The daily amount that suits you depends on your weight, your kidney function and the condition being treated, and the screening interval depends on your own risk factors. Talk to your physician before starting, changing or stopping any treatment described here, and to an ophthalmologist about the timing of retinal screening.