
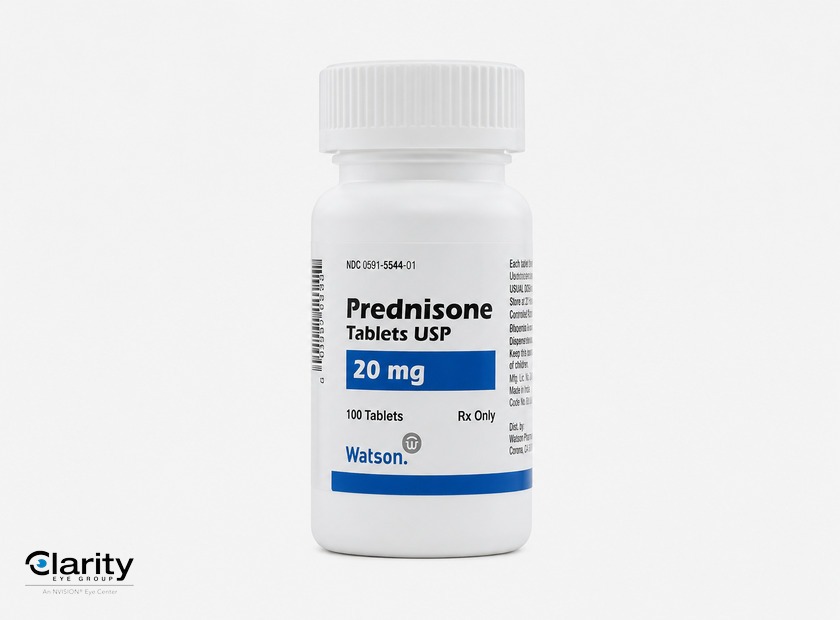
Buy Prednisone online — the corticosteroid that calms swelling in the airways, joints, skin and gut when your own immune response turns on you. Most people meet it during a flare of something else. The tablets are cheap and the relief is real. Almost every question that follows is about what happens next.
| Name | Strength | Starting Price |
|---|---|---|
| Prednisone (Deltasone) | 1 mg · 5 mg · 10 mg · 20 mg | From $0.32 per tablet |
What this page covers
When a short course earns its place
Inside a five-day burst
Dosage across six strengths
Buying online and what it costs
Side effects by dose and by time
The eye on both lists
Constipation and diarrhea
The afternoon blood sugar climb
Adrenal glands after week three
Getting back to normal
Prednisone Turns Down an Immune System in Overdrive
Prednisone lowers inflammation by damping your own immune response. It does that job well, and a short course is usually tolerated without much trouble. What it does not touch is the cause. Pollen, a virus, an autoimmune misfire — all of it is still there when the course ends. Swelling settles, heat leaves the joint, the airway opens.
People who buy Prednisone online usually know that part already. Timing is what surprises them. Blood levels peak one to two hours after the tablet. Relief lags well behind that peak, because the effect works by changing which genes a cell reads. Airway swelling responds within hours. Joints and skin often take a day or more.
The tablet is also inactive when you swallow it. An enzyme in the liver called 11-beta-HSD1 converts it into prednisolone. Only then does it bind anything. For almost everyone that step is silent. It stops being silent in cirrhosis and active liver injury, where measured conversion runs lower than expected. Liver numbers change what a course does before the first tablet is taken.
Conditions Where a Short Steroid Course Earns Its Place
Short courses earn their keep when inflammation itself is the emergency. Not the infection behind it, not the allergen, the swelling. Prednisone covers an unusually wide range of conditions. That range is the reason it gets misread.
- Asthma and COPD flares, where a swollen airway is the immediate danger
- Severe allergic reactions and contact rashes, including poison ivy
- Gout attacks when anti-inflammatories cannot be used
- Rheumatoid arthritis and polymyalgia rheumatica flares
- Ulcerative colitis and Crohn’s flares that have escaped maintenance therapy
- Adrenal insufficiency, where the tablet replaces a hormone rather than suppressing one
Sinus infections and bronchitis sit in a different category. A steroid shrinks swollen tissue and makes breathing easier. That is genuinely useful. It does nothing to the organism causing the problem. Taking one for a chest infection treats the swelling, not the bug. That matters when symptoms return four days later.
Bowel conditions behave differently again. There the medication buys time while a maintenance plan takes hold. Nobody stays on a steroid for ulcerative colitis by design.
Inside a Five-Day 20 mg Course
The five-day course is the shape most people meet first. One 20 mg tablet each morning is the simplest version, then nothing. Many prescriptions double that to 40 mg a day. No stepping down, no taper, no adrenal problem afterwards. Five days is short enough that the withdrawal question never opens.
A flat pattern like that is called a burst. Inflammation responds better to a decisive dose than a cautious one. Shorter exposure also means fewer of the slow problems appear. At 40 mg the two tablets can go in together or split morning and evening. Some courses run six days rather than five. The arithmetic barely changes.
A prednisone dose pack works on a different principle. Instead of a flat dose it steps down day by day. Six tablets on the first morning, then five, then four, until the card is empty. Twenty-one tablets is the usual count. That step-down looks reassuring but changes very little over a week. The adrenal glands were never suppressed in the first place.
A dose pack helps with compliance. Tablets are laid out by day, so nothing needs counting.
Taking 20 mg for five days still leaves a footprint. Sleep is usually the first thing to go. That is why the whole dose goes in early rather than at night. Appetite rises. So does blood sugar, in a pattern worth its own section below. None of that is a reason to skip a course a flare needs.
Prednisone Dosage Across Six Tablet Strengths
Prednisone dosage starts with the tablet. Six strengths exist and most pages mention three. The approved label lists 1 mg, 2.5 mg, 5 mg, 10 mg, 20 mg and 50 mg tablets. Large ones serve the start of treatment. Small ones serve the hardest part of any long course.
| Strength | Where it is normally used |
|---|---|
| 1 mg | Final steps of a long taper where a whole 5 mg drop is too big |
| 2.5 mg | Half-steps down to nothing and low-dose maintenance |
| 5 mg | Maintenance dosing and the building block of most dose packs |
| 10 mg | Moderate courses and the middle of a step-down schedule |
| 20 mg | Short bursts for flares and the most commonly dispensed strength |
| 50 mg | High-dose starts so a 60 mg day needs fewer tablets |
Strengths as listed on the DailyMed label for prednisone tablets USP. Checked August 2026.
Strength on the bottle is not strength across the class. Five milligrams of prednisone does not equal five of anything else.
| Steroid | Equivalent anti-inflammatory amount |
|---|---|
| Hydrocortisone | 20 mg |
| Prednisone | 5 mg |
| Prednisolone | 5 mg |
| Methylprednisolone | 4 mg |
| Dexamethasone | 0.75 mg |
Equivalent anti-inflammatory amounts as tabulated in the NCBI Endotext reference. They match potency only, not how long each steroid acts. Checked August 2026.
Anyone tapering from a long course will need 1 mg or 2.5 mg tablets eventually. Those are also the strengths a pharmacy is least likely to keep in stock, and running out of them stalls a taper at 5 mg for months.
Where the Line Sits Between Low and High
Daily amounts of prednisone in the label run from 5 mg to 60 mg. Condition decides the figure, not body weight. Within that range the working thresholds are consistent. A low dose is under 7.5 mg a day. The middle band runs from 7.5 mg to 30 mg. A high dose starts above 30 mg. Anything past 60 mg is reserved for situations where an organ is at risk.
So is 20 mg a low dose? No, though it is not a high dose either. It sits in the middle band, which is why it turns up so often. Calling 20 mg a low dose sets the wrong expectation. The amount is usually enough to break a flare. It is also modest enough that five days need no step-down.
Two other numbers matter more than the label ranges. The first is 20 mg a day. Past two weeks at that level the immune effect counts as immunosuppression. The second is 7.5 mg, roughly what a healthy body makes on its own. Below that line the tablets replace your own output instead of overriding it. That changes what stopping means.
Buy Prednisone Online and What It Costs Per Tablet
You can buy Prednisone online with a valid prescription. Two things set what you pay. One is the strength on the label, the other is how many tablets are in the pack. Both move further than people expect.
Acquisition figures come from NADAC, the federal acquisition-cost benchmark CMS publishes weekly, effective 19 August 2026. Counter prices come from SingleCare’s survey, May 2026. Totals are per-tablet times quantity.
The distance between those two blocks is the whole picture. A pharmacy buys ten 20 mg tablets for about seventy-seven cents and sells them for sixteen dollars. Neither figure is a discount. Decades off patent and dozens of manufacturers are what put the acquisition cost in pennies.
Dose packs carry a premium of their own. That same 10 mg tablet costs a pharmacy six cents loose and fifty-three cents inside a twenty-one tablet pack. Nine times the price buys the days printed on a card. Anyone comfortable counting tablets is paying for cardboard.
Read the quantity column as a course calculation. A five-day burst takes ten 20 mg tablets. Someone steady on 5 mg uses thirty a month, so ninety covers a quarter and lines refills up with a three-month review. Prednisone cost without insurance never becomes a real barrier at these numbers.
Where you order matters less for price than whether the pharmacy behaves like one. A licensed pharmacy asks for a prednisone prescription online. It either requests one from your prescriber or takes an upload of the one you hold. Expect questions about other medications, particularly anti-inflammatories. A pharmacist should be reachable by phone, not only by contact form.
Prednisone over the counter is one of the most searched phrases attached to this medication. The answer has never changed. It is prescription-only in every American state. A site selling it without one is telling you what kind of operation it runs. The low price then costs you nothing in safety.
Brand and generic sit side by side at any pharmacy. Deltasone is the name these tablets carried for decades, and the medication has been in continuous use since the 1950s. Generic tablets hold the same active ingredient at the same strengths. They fill almost every American prescription today. Either form works and the tablets behave the same way.
Which Side Effects Track Dose and Which Track Time
Prednisone side effects split cleanly into two groups. One tracks how much you take. The other tracks how long you take it. Most pages list them in a single column, which hides the split entirely.
| Driven by dose size | Driven by course length |
|---|---|
| Insomnia and vivid dreams | Bone density loss |
| Raised blood sugar | Thinning skin and easy bruising |
| Hunger and food cravings | Fat moving to the face and trunk |
| Raised blood pressure and fluid retention | Weakness in the thigh and shoulder muscles |
| Mood swings and restlessness | Adrenal suppression |
| Raised eye pressure | Posterior subcapsular cataract |
Left column effects appear within days and fade within days of stopping. Right column effects need weeks to develop and weeks to months to reverse.
Read that table again with a burst in mind. Everything on the left is in play. Almost nothing on the right is, because five days cannot build any of it. That is the whole argument for keeping courses short.
Weight gain straddles both columns, which is why it confuses people. The first few pounds are fluid and show up within a week. Redistribution that rounds the face takes months. Tiredness splits the same way, early from broken sleep and later from muscle loss.
The right-hand column is where planning pays. Bone loss is fastest in the first three to six months, before anyone has thought to measure it. Calcium and vitamin D belong in the plan from the start rather than after a scan. Broken sleep on steroids deserves the same early attention. It responds better to timing changes than to anything added on top.
Prednisone Treats the Eye and Also Damages It
The label carries the eye twice, on two lists that contradict each other on the surface. Ophthalmic diseases sit among the approved indications: optic neuritis, diffuse posterior uveitis, iritis and iridocyclitis, keratitis, sympathetic ophthalmia. Under adverse reactions the same document records posterior subcapsular cataracts, increased intraocular pressure, glaucoma and exophthalmos. Both entries are earned.
The damage runs on the same two clocks as the table above. Cataract belongs in the duration column. It forms at the back of the lens over months of continuous treatment, it scatters light worst in bright sun and oncoming headlights, and it does not clear when the course ends. Raised pressure belongs in the dose column. It climbs within weeks, it produces no symptom at all while it does so, and in most people it settles once the steroid stops.
Not every eye responds that way. A minority react to steroids with a sharp rise in pressure, and nobody knows which group they belong to until somebody measures it. That matters most for anyone already being watched for glaucoma, where a course of tablets can undo months of control without announcing itself.
One more line deserves reading twice. Steroids may enhance secondary ocular infections due to fungi or viruses, and the label says so plainly. A red eye treated as inflammation when the real cause is a virus on the cornea gets worse rather than better. A red eye that appears during a course belongs in front of somebody who can look at it properly rather than in a longer prescription.
A five-day burst builds none of this. Prolonged use is the phrase the label chooses, and it means what it says. Anyone whose course is measured in months rather than days is worth a baseline pressure reading and a look at the lens before the third month rather than after it.
Can Prednisone Cause Constipation or Diarrhea?
Yes to both, and they arrive by unrelated routes. Diarrhea tends to belong to the first days. Constipation belongs to the long courses. Its mechanism runs through the kidneys rather than the bowel.
Loose stools early on trace back to direct irritation of the stomach and upper bowel. The appetite surge helps them along, because people eat differently for a week. It tends to settle within a few days. Taking the tablets with food blunts it in most cases.
Constipation follows a slower path. Steroids make the kidneys hold sodium and lose potassium. Falling potassium slows the muscle work that moves stool along. That is why constipation on a long course arrives alongside ankle swelling and a few pounds of fluid. The three share one cause.
Neither pattern is a reason to stop treatment early. Both are worth tracking. A bowel that changes habit mid-course can be telling you something about the condition being treated. In inflammatory bowel disease especially, new diarrhea is a signal to look at rather than a side effect to accept.
The Ulcer Risk That Only Shows Up With Ibuprofen
Steroids have a reputation for causing ulcers. The evidence has never really supported it. Taken alone, prednisone raises the measured risk only slightly. Add ibuprofen or another anti-inflammatory and the picture changes completely.
Case-control work on corticosteroid use and peptic ulcer disease found the same shape more than once. A steroid on its own sat near the bottom of the range. Some analyses found almost no increase, others around 1.8 times baseline. An anti-inflammatory alone sat around four times baseline. Together they landed far above either, at roughly nine times in one dataset and higher in another. The combination does not add up. It multiplies.
This is why gastroenterology bodies recommend acid suppression for people taking both. They do not recommend it routinely for a steroid on its own. Anyone already taking ibuprofen daily or low-dose aspirin belongs in the first group. So does anyone reaching for ibuprofen to treat the same flare. Acetaminophen sits outside the problem entirely and is the safer choice for pain.
What Alcohol Adds to the Stomach Risk
Alcohol and prednisone do not interact in the pharmacological sense. Neither changes how the other is broken down. What they share is a target. That target is the lining of the stomach.
A steroid slows the repair of that lining. Alcohol irritates it directly. Over five days a drink or two is unlikely to cause anything you would notice. Across weeks the two pull in the same direction and the stomach loses ground. Add an anti-inflammatory and it loses ground faster.
There is a second overlap that gets missed. Alcohol breaks up the second half of the night, and a 20 mg morning dose is already doing that. Someone awake at three will not be helped by a nightcap.
Why Blood Sugar Climbs in the Afternoon Not at Dawn
A morning prednisone dose does not raise blood sugar evenly through the day. It produces a peak roughly six to nine hours later, in the afternoon and early evening. Overnight the numbers often drift back down on their own. Almost nobody explains that timing, and it changes how a reading should be judged.
That timing catches people out. Fasting glucose is the number most home meters get used for. It is measured at exactly the wrong moment. A reading can look entirely normal on a morning when the afternoon figure was well above target. Continuous monitoring during steroid treatment shows the pattern clearly.
Two mechanisms drive it. The liver is pushed to release more glucose. Muscle and fat become less responsive to insulin. Both scale with the amount taken. Above roughly 50 mg a day the rise often needs active management rather than watching.
If you already live with diabetes or prediabetes, the practical change is simple. Test in the late afternoon during a course, not only before breakfast. Without that history, five days is unlikely to leave any trace. Longer treatment is a different question. These glucose changes respond to meal timing and composition more than people expect.
Your Adrenal Glands After the Third Week
Your body makes its own steroid every day. Tablets supply it from outside, and the signal driving your own production quietly switches off. Past about three weeks of prednisone above 20 mg, assume the switch has flipped.
What follows is not damage. The adrenal cortex has stopped being asked to work and shrunk to match. It restarts when the signal returns, but slowly. That lag is why a long course cannot be stopped the way a short one can.
Stopping abruptly after a long course is the real danger. Without its own supply and without the tablets, the body has neither. Fatigue, nausea, low blood pressure and dizziness follow, and at the severe end this becomes an adrenal crisis. Any treatment past three weeks comes down in steps.
Recovery has a measured timeline. The Endocrine Society recommendations on glucocorticoid-induced adrenal insufficiency put most recovery between four and ten weeks after the last dose. Roughly one person in eight is still not fully recovered at twenty weeks. Higher amounts and longer treatment push the whole curve to the right, and there is no way to hurry it.
Two other hormone systems shift during high-dose treatment. Both get misread. Thyroid results come first. A high dose suppresses TSH and slows the conversion of T4 into active T3. Panels drawn mid-course can suggest a thyroid problem that is not there. That is a poor moment to change a levothyroxine dose. Such a panel is worth reading alongside what we see in thyroid disorders rather than in isolation.
Sex hormones come second. Sustained exposure suppresses the axis driving testosterone and the menstrual cycle. Long treatment often brings low libido, irregular periods or fatigue unrelated to sleep. Those effects are usually reversible. That is why male and female hormone testing is worth repeating after a course rather than during one.
Vaccination runs on that same 20 mg threshold. Live vaccines are usually deferred until the amount comes down. Inactivated ones carry no such restriction at any level.
The Cortisol Number That Ends a Taper
Most advice about tapering stops at the word slowly. An actual number sits underneath it. That number is a morning cortisol level, drawn before the day’s tablet.
The logic runs like this. Once a taper reaches the physiological band described earlier, the tablets suppress nothing. They stand in for what the adrenal glands should be producing. Recommendations put the last safe step somewhere around 3 to 6 mg of prednisone. Dropping below that line before the glands restart is what turns a taper into a withdrawal. Morning cortisol is how that gets checked rather than guessed. A low result means holding at the current step. Comfortable numbers mean the last drop is safe.
Withdrawal symptoms are unmistakable once you know the shape:
- Deep fatigue that sleep does not fix
- Aching joints and muscles without a flare to explain them
- Nausea and loss of appetite
- Low mood and irritability
- Light-headedness on standing, sometimes a low-grade fever
Withdrawal like this appears even when a cortisol result looks acceptable. The body adapted to a higher level than it now has. Slowing the taper rather than reversing it is the usual answer. That ongoing support is the work described under adrenal insufficiency. It includes cover for illness and surgery, which a recovering axis cannot answer alone for months.
How Long Does It Take to Feel Like Yourself Again?
Prednisone itself is gone within about a day of the last tablet. Nothing else runs on that clock. The mismatch is why this question gets asked so often. What follows is the usual order.
- Days: sleep, appetite and blood sugar reset
- One to two weeks: fluid drops away with the puffiness and the first few pounds
- Weeks: mood settles, sometimes through a flat patch in the middle
- Months: skin, muscle and a rounder face return to baseline
- Months and longer: adrenal output and bone density, the two slowest of all
After a burst almost none of that applies. You take the tablets, the flare breaks, and within a week the episode is behind you. That is the version most people experience. It is worth saying plainly, because the long-course picture dominates everything written about this medication.
After a long course the arc runs in months. The last stretch is mostly adrenal, and energy comes back last. Knowing that in advance turns an alarming few weeks into an expected few weeks. Repeated steroid courses are themselves worth reviewing as a pattern. Becoming a new patient is where that starts.
Medical Disclaimer
This page is written for general information and does not replace individual medical advice. Prednisone is a prescription medication. Dosing, course length and tapering schedules are decided case by case. Please consult your doctor before starting, changing or stopping any steroid treatment.