
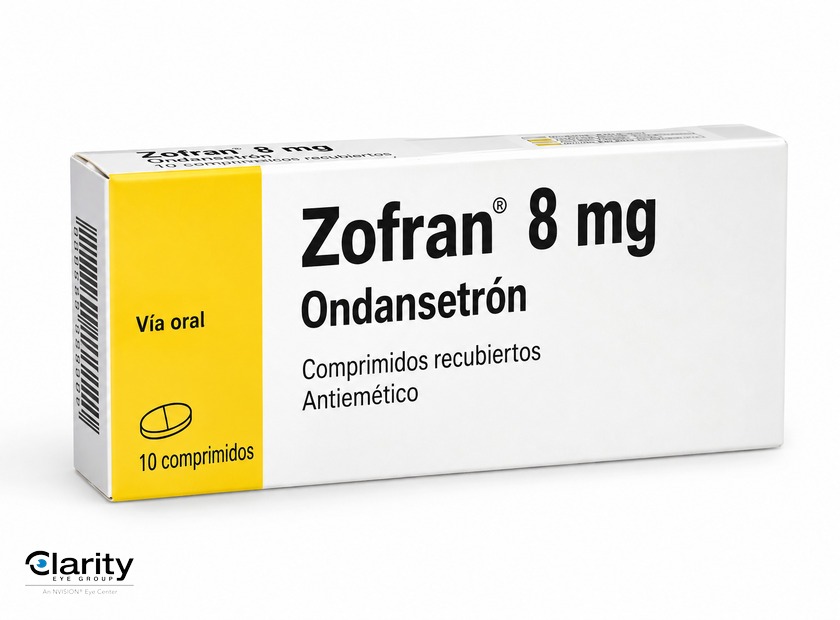
Buy Zofran online when nausea comes from chemotherapy, radiation, anesthesia or a stomach virus, since ondansetron blocks the gut serotonin behind it. That list is not arbitrary. Every entry on it shares one trigger, and the conditions missing from it share a different one. What follows traces that split from the receptor down to the prescription.
| Name | Strength | Starting Price |
|---|---|---|
| Zofran (ondansetron) | 4 mg · 8 mg · ODT | From $0.09 per tablet |
What this page covers
Why Nausea Starts in the Gut Wall Not the Head
The signal begins in the lining of your small intestine. Enterochromaffin cells sit wedged in that lining. They release serotonin whenever they meet a threat. A norovirus particle counts. So does a cytotoxic chemotherapy agent. The released serotonin lands on 5-HT3 receptors along nearby vagus nerve endings. The vagus carries that alarm up to the brainstem.
Ondansetron reaches those receptors first and occupies them. Serotonin still pours out of the gut lining, yet it has nowhere left to bind, so the message never travels. Pharmacologists call this competitive antagonism rather than sedation. The distinction shows up in how the medication feels. You stay alert while the queasiness recedes without the woolly heaviness that older remedies leave behind.
A second interception point sits higher up. The chemoreceptor trigger zone in the medulla carries its own dense field of 5-HT3 receptors. Ondansetron reaches those as well, and blocking both ends of the loop explains a great deal about its reliability. One 8 mg tablet can flatten nausea that started three feet lower in the body. The pharmacology of ondansetron has been mapped since 1991, when GlaxoSmithKline first brought the compound to market.
Most people who buy zofran online are treating exactly this kind of trigger. Chemotherapy, radiation, anesthesia and stomach viruses all set off the enterochromaffin release. Vertigo and car sickness do not, because those signals travel through the vestibular system rather than the gut. That system speaks a histamine and acetylcholine dialect, and 5-HT3 blockade cannot hear a word of it. One fact predicts almost every disappointed review this medication has ever received.
Nausea and vomiting are not the same event. Vomiting is a motor reflex coordinated by the brainstem, while nausea is the conscious sensation assembled from that same stream of input. Ondansetron interrupts that input, so it addresses both at once. Remedies that act only on the stomach lining address neither.
Ondansetron is the generic name and Zofran is the original brand. The molecule also appears as an orally disintegrating tablet. There is an oral soluble film and a clear injectable solution. All four deliver the same compound to the same receptor. Only the delivery route changes.
Conditions Where Ondansetron Earns Its Place
Three approved uses carry the strongest evidence. Chemotherapy-induced nausea leads, radiation-induced nausea follows, and postoperative nausea after general anesthesia completes the set. All three share the mechanism described above. Emergency departments have also leaned on ondansetron for acute gastroenteritis for two decades. That use sits off-label, yet it has become so routine it feels official.
Situations where the medication tends to deliver:
- Viral gastroenteritis. Norovirus and rotavirus injure the gut lining directly. Injured lining releases serotonin. One dose often restores the ability to keep fluids down.
- Food poisoning. Bacterial toxins act on the same enterochromaffin cells. Relief is symptomatic and does not shorten the illness.
- Gastroparesis flares. Delayed emptying stretches the stomach wall. That stretch triggers vagal firing which ondansetron can quiet.
- Migraine-associated nausea. Often paired with a triptan. That combination needs a caution covered further down.
- Post-anesthesia recovery. Given before the procedure rather than after. Prevention works better than rescue here.
Diarrhea deserves a separate note. The search volume around it suggests real confusion. Ondansetron is not an antidiarrheal. It does slow colonic transit, but only as a side effect of 5-HT3 blockade, so stools may firm up while you take it. That result is downstream rather than therapeutic. Loperamide and bismuth remain the right choices when diarrhea leads the picture.
Ondansetron rarely works alone in oncology. Chemotherapy protocols combine it with dexamethasone and often with an NK-1 antagonist such as aprepitant, because each agent covers a different phase of the emetic response. The 5-HT3 blocker handles the first 24 hours, while delayed nausea on days two and three runs through pathways ondansetron barely touches.
Fever and diarrhea in a child change the calculation. Ondansetron helps a child keep oral rehydration solution down. That single outcome is what emergency physicians measure. It does not treat the infection and it does not shorten it.
Patients who buy zofran online for a hangover are similarly off target. Alcohol-related nausea comes largely from acetaldehyde and direct gastric irritation, and serotonin release plays only a minor part in it. Some people report benefit anyway. The evidence for it stays thin.
Anxiety-driven queasiness sits in the same uncertain category. Small trials have looked at 5-HT3 blockade for anxiety. Results were mixed. None of them support this medication as a primary treatment.
Prescription Status and the Over the Counter Question
No. Ondansetron requires a prescription everywhere in the United States. That applies to every form and every strength. People ask can you get zofran over the counter almost as often as they search the brand name. The answer has not changed since approval. No pharmacy chain, warehouse club or online retailer may sell it from an open shelf.
The reason is cardiac rather than commercial. Ondansetron lengthens the QT interval in a dose-dependent way. A small group of people carry a predisposition that turns that lengthening into a dangerous rhythm. Some inherit that vulnerability while others acquire it from another medication, and a prescriber can screen for both where a shelf cannot. Anyone asking can you buy zofran over the counter is really asking whether the screening step can be skipped.
Worth knowing: Ondansetron masks vomiting without treating its cause. In appendicitis, bowel obstruction or a serious head injury, suppressed vomiting can delay recognition of the real problem. That is a second argument for prescriber involvement rather than self-selection.
The shelves do hold alternatives. They work through different receptors. Dimenhydrinate and meclizine target the vestibular pathway, and both genuinely outperform ondansetron once motion sickness is the problem. Bismuth subsalicylate coats an irritated stomach lining. Ginger has modest trial support for pregnancy queasiness. None of them touch chemotherapy nausea.
This also explains why the shelf remedies disappoint during a stomach virus. Bismuth and antihistamines were designed for a different problem, and neither reaches the receptor that gastroenteritis actually activates. Households that buy zofran online and hold a small supply against the next norovirus season are responding to that gap rather than to marketing.
Insurance status changes nothing about the requirement. Paying cash does not either. Pharmacies that dispense zofran online verify the prescription against a licensed prescriber before anything ships. Sites that skip that step are not pharmacies in any legal sense.
So the practical route runs through a consultation first. That step is quicker than most people expect. The section below walks through it.
Buy Zofran Online Through a Licensed Pharmacy
A legitimate online pharmacy asks for a prescription before it asks for payment. That single behavior separates the pharmacies worth using from the rest. Some sites offer ondansetron with no prescription and no consultation. Those operate outside United States law. Tablets arriving from such a source carry no guarantee of identity, strength or purity.
Verification is straightforward. A licensed pharmacy displays its state license number and lists a physical dispensing address. It provides a way to reach a pharmacist, and it carries accreditation you can check independently. People who buy zofran online through such a pharmacy usually pay less than at a walk-in counter. Generic competition since 2006 explains most of that gap.
Turnaround is the other common question. Most patients who get zofran online finish the questionnaire and the consultation on the same day. Standard shipping then takes two to five business days. Anyone planning to buy zofran online ahead of a chemotherapy cycle should allow for that window rather than ordering during treatment week.
Steps to Order Zofran Online Without Guesswork
The sequence below reflects how a compliant pharmacy actually processes a request:
- Complete the medical questionnaire. It covers your nausea pattern, current medications, cardiac history and any family history of arrhythmia.
- Consult a licensed prescriber. This happens by video or secure message. The QT question gets settled here.
- Receive the prescription electronically. Strength, quantity and refill count are fixed at this stage.
- Choose your form and pack size. Standard tablets, disintegrating tablets and oral film differ in price and in how you take them.
- Confirm the shipment. Tablets stay stable at room temperature and need no cold chain.
One detail catches people out. Anyone hoping to order zofran online for a stomach virus already underway is fighting the clock. The consultation and shipping together outlast the illness. Ondansetron proves far more useful held in reserve.
What Thirty Tablets Cost by Route
Three routes explain almost every quote you will see for this medication. Every figure below is published rather than estimated.
Cash prices and the struck-through retail comparison come from Mark Cuban Cost Plus for the 4 mg and 8 mg tablets. Acquisition figures are the national average published by CMS in its NADAC file. All checked in August 2026.
The spread is the whole story. A cash payer at a transparent pharmacy lands within a few dollars of what the pharmacy itself paid, while the same thirty tablets carry a three-figure tag at ordinary retail. Ninety-tablet orders push it further still, taking 4 mg to roughly $0.09 per tablet and 8 mg to $0.16. Wafers run about double the plain tablet at both strengths, which is worth weighing if swallowing is not the problem.
Brand Zofran and Generic Ondansetron Compared
The active molecule is identical. Generic ondansetron entered the American market in December 2006, when the original patent expired. Every version since has had to prove bioequivalence within a tight statistical window. Blood levels track the same curve and onset tracks the same curve, while price follows a completely different one.
What genuinely differs sits in the inactive ingredients. Disintegrating versions rely on mannitol and aspartame for sweetness. That matters if you have phenylketonuria. Some tablet coatings use lactose. A few contain dyes that provoke reactions in a small number of people.
Patients who buy zofran online sometimes switch manufacturers between refills. A wafer may taste different or melt at a different speed, and excipients explain nearly all of that variation. The clinical effect stays the same.
Brand Zofran is still manufactured. It has become uncommon in retail pharmacy. Insurers rarely cover it while a generic exists, and cash-paying patients almost never choose it on their own. The price gap for the same 8 mg tablet can exceed tenfold.
The disintegrating form kept its premium longer than the plain tablet. Generic wafers arrived later and involved more complex manufacturing, so that gap has narrowed without ever closing. Plain tablets remain the cheapest route to the same molecule.
Identifying which generic you hold is simple enough. Every tablet carries an imprint code, and the bottle label lists a national code that identifies the manufacturer, the strength and the pack size. Comparing those two details between refills settles most questions about whether the pharmacy quietly changed suppliers.
One caveat is worth carrying forward. If a particular generic suits you, ask your pharmacy to keep supplying that manufacturer. Removing an unnecessary variable helps when you are already tracking side effects.
How Much Ondansetron Each Situation Calls For
Adult oral dosing runs from 4 mg to 24 mg. The amount depends entirely on what is causing the nausea. The schedule varies just as much. A single 24 mg tablet before highly emetogenic chemotherapy is standard. An 8 mg tablet three times daily suits radiation therapy. Postoperative prevention uses 16 mg one hour before anesthesia. The approved product labeling separates these deliberately.
| Situation | Oral dose | Timing |
|---|---|---|
| Highly emetogenic chemotherapy | 24 mg once | 30 minutes before treatment |
| Moderately emetogenic chemotherapy | 8 mg twice | 30 minutes before then 8 hours later |
| Radiation therapy | 8 mg three times daily | First dose 1 to 2 hours before |
| Postoperative prevention | 16 mg once | 1 hour before anesthesia |
| Children 4 to 11 years | 4 mg three times daily | 30 minutes before then 4 and 8 hours later |
| Age 12 and older | Adult dosing | By indication above |
Children under four are dosed by weight rather than by tablet. Liquid and disintegrating forms therefore dominate pediatric use, and emergency departments commonly give a single weight-based dose for gastroenteritis. The child then goes home without a continuing supply. Repeated dosing in young children stays a prescriber decision.
Liver function sets the only hard ceiling. In severe hepatic impairment the total daily amount should not exceed 8 mg, because clearance drops steeply and the compound accumulates. Kidney function has almost no effect on dosing. That surprises people who expect both organs to matter equally.
Disintegrating tablets are dosed exactly like the ones you swallow, which trips people up more often than it should. A 4 mg wafer delivers 4 mg, and a 8 mg wafer delivers 8 mg. Nothing about the format changes the arithmetic, and taking two wafers to compensate for a perceived weaker effect simply doubles the exposure.
Strength is the first decision facing anyone who wants to buy zofran online, and it follows the indication rather than personal preference. Timing beats quantity for prevention. A dose taken before the trigger outperforms the same dose taken after vomiting starts. Chemotherapy protocols are built around that fact. So is preoperative dosing.
Doses spaced closer than four hours apart add little. Receptor occupancy is already near its plateau at standard amounts. Extra tablets raise cardiac exposure without raising relief. That plateau is why maximum single doses exist at all.
Minutes to Relief and Hours of Cover by Form
A swallowed tablet begins working in about 30 minutes. It peaks near the two-hour mark, while injectable ondansetron acts within 5 to 10 minutes of administration. Hospitals reach for it when someone cannot keep anything down. Relief from a single oral dose usually holds 8 to 12 hours. The elimination half-life sits around 4 hours in healthy adults. After 65 it stretches toward 5 or 6 hours.
The orally disintegrating tablet causes the most confusion. It melts on the tongue within seconds, so it feels faster. Absorption still happens in the intestine rather than through the lining of the mouth. Onset therefore matches the standard tablet almost exactly. Its real advantage is mechanical. You can take it during active vomiting without water.
Form by form: Standard tablet — cheapest per dose, needs water, onset around 30 minutes.
Orally disintegrating tablet — dissolves on contact, no water required, same onset, fragile packaging.
Oral soluble film — thin strip, discreet, useful for children who refuse tablets, priciest option.
Injectable solution — clinic and hospital use only, onset under 10 minutes, highest QT signal.
Food changes very little. A meal slows absorption slightly and raises the total amount absorbed by a small margin, and neither shift is clinically meaningful. Take it with breakfast or without.
Water is a different question and a common one. No waiting period follows a standard tablet. Sipping slowly rather than gulping does reduce the chance of bringing the tablet back up. After a disintegrating version, let it dissolve fully before you drink.
True tolerance does not develop in the way it does with sleep or pain medications. Receptor sensitivity holds steady across a course, so a dose that worked in week one should still work in week four. Fading benefit therefore reflects a changing trigger rather than a fading medication, and that difference is worth naming out loud before anyone escalates the dose.
Duration explains most dosing schedules. Eight hours between doses matches how long meaningful receptor blockade lasts. Nausea returning at hour six suggests the trigger is stronger than one dose can cover. That is a reason to review the plan rather than to add tablets.
What Most People Feel in the First Few Doses
Headache tops the list and affects roughly one in four users. It arrives within a couple of hours. The pain tends toward dull rather than sharp, and acetaminophen usually settles it within an hour. Constipation comes second at around one in ten. Fatigue and mild dizziness round out the group worth expecting.
Drowsiness deserves a clarification. So many people search for it that the confusion is clearly widespread. Ondansetron is not sedating the way promethazine or dimenhydrinate are. It does not act on histamine receptors at all. The tiredness people report is often secondhand, since relief after hours of retching leaves anyone thoroughly exhausted. Some genuine fatigue does occur, and consumer medication information lists it among expected effects. Heavy sedation points to something else in the mix.
Rarer reactions justify attention. The label is blunter about the eye than most summaries built on it. It records cases of transient blindness, predominantly during intravenous administration, resolving anywhere between a few minutes and 48 hours. Tablets are not where that happens. The same postmarketing list carries oculogyric crisis, a forced upward turn of both eyes that usually arrives alongside other dystonic reactions. Both resolve, and neither argues against the medication. They are worth naming so that nobody mistakes either one for something structural. Liver enzymes rise modestly in a minority of patients on repeated dosing. Serious rhythm disturbance stays genuinely uncommon at oral doses in people with a normal baseline electrocardiogram. It is still the reason the 32 mg single intravenous dose left the market in 2012.
Medications That Clash With Ondansetron
One combination is off limits. Apomorphine taken alongside ondansetron has produced profound hypotension and loss of consciousness. The pairing is contraindicated outright. Everything else falls into two manageable groups.
Serotonin load comes first. Ondansetron blocks one serotonin receptor subtype and leaves the others exposed. SSRIs, SNRIs, triptans, tramadol, linezolid and St John’s wort all raise the theoretical risk of serotonin syndrome. Reported cases stay rare and usually involve several agents at once. Agitation, tremor, sweating and a racing pulse within hours of a new combination warrant an urgent call.
Cardiac conduction comes second. Several medication classes already stretch the QT interval. Certain antiarrhythmics do, and so do some antipsychotics, methadone and a handful of common antibiotics. Each adds to what ondansetron contributes. A prospective emergency department study measured QTc prolongation after a single intravenous dose. Low potassium or magnesium amplifies the same effect.
Two enzyme inducers are easy to overlook. Rifampin, phenytoin and carbamazepine speed up ondansetron clearance, and a standard dose can quietly underperform as a result. Tramadol runs the opposite way. Ondansetron blunts its pain-relieving effect, and patients on both sometimes need more tramadol than expected.
Alcohol carries no direct interaction. It does irritate the stomach lining. That works against the very symptom you are trying to settle.
Why the Gut Slows Down on Ondansetron
Constipation is not an incidental annoyance here. It is the direct footprint of the mechanism that stops the nausea. Serotonin does more than signal alarm through the vagus, since it also drives the peristaltic reflex that moves contents along the colon. Block 5-HT3 receptors and colonic transit slows measurably.
Pharmacology confirms the link from the opposite direction. Alosetron is a close relative of ondansetron. It is licensed specifically to slow the gut in severe diarrhea-predominant irritable bowel syndrome. Same receptor family. Same slowing. Deliberately harnessed. Taking ondansetron for nausea means accepting a smaller version of that effect.
This matters most for people whose digestion already runs sluggish. Hypothyroidism slows transit, and so do constipation-predominant irritable bowel syndrome and long-term opioid therapy. Each starts you from a lower baseline, and a week of ondansetron can tip a manageable pattern into an uncomfortable one.
Course length is the practical lever. Three days of dosing rarely causes trouble. Three weeks often does. Chemotherapy patients feel this most, because their schedule is measured in cycles rather than days.
Magnesium citrate has a useful dual role for this specific problem. It draws water into the bowel and corrects a deficiency that worsens motility on its own. Timing meals to your least nauseated hours helps too. A stomach that tolerates food tolerates fiber, and fiber only works while it keeps moving.
Transit returns to baseline within a few days of stopping. Constipation that persists after the course ends signals something else was already at work.
Is Ondansetron Safe During Pregnancy
It is widely used, reasonably well studied and not the first choice. Obstetric guidance places vitamin B6 with doxylamine ahead of it, reserving ondansetron for cases where that pairing fails or where dehydration threatens. That ordering reflects a genuine safety question rather than an abundance of caution.
The specific concern is oral clefts. A cohort study of more than 1.8 million pregnancies found no increase in cardiac malformations after first-trimester exposure. The relative risk came out at 0.99, while oral clefts showed a modest signal at 1.24. That translates to roughly three extra cases per 10,000 births. Later systematic reviews called the finding small and not fully consistent across datasets.
Untreated hyperemesis carries its own weight in the calculation. Sustained vomiting produces dehydration and electrolyte loss, with weight loss and thiamine depletion following close behind. Severe cases end in hospital. Obstetric organizations weigh that reality against a marginal cleft signal. For women who cannot hold down fluids the balance usually favors treatment.
Dosing During Pregnancy at a Glance
Obstetric practice favors the smallest amount that restores oral intake. That commonly means 4 mg every eight hours as needed. Fixed schedules are used less often. Stepping up to 8 mg happens only when 4 mg proves insufficient. Many prescribers avoid the first trimester where symptoms allow, since organ formation and the cleft window fall in those same weeks.
Two practical notes follow. Constipation compounds an already common pregnancy complaint, so the motility issue above deserves extra attention here. A few doses during a bad week is also a different proposition from continuous use across a whole trimester.
Small amounts pass into breast milk. The quantity is low, and no consistent effect on nursing infants has been documented to date. Postpartum use is therefore treated far less restrictively than use in early pregnancy.
When Nausea Keeps Coming Back Look Deeper
Nausea that returns every few weeks is a symptom. Ondansetron treats the symptom rather than whatever generates it. A stomach virus resolves on its own and a course of chemotherapy eventually ends. Nausea that outlasts an obvious cause by months belongs in a different conversation altogether.
Delayed gastric emptying leads the list of causes. Gastroparesis produces early fullness, bloating and nausea that worsens through the day. Diagnosis relies on a gastric emptying study rather than symptom pattern alone. Diabetes is the most familiar cause, and post-viral damage to the vagus nerve is the most frequently missed one.
Other patterns that repeatedly turn out to be the real driver:
- Small intestinal bacterial overgrowth. Fermentation produces distension. Distension produces nausea that antiemetics only mask.
- Gallbladder dysfunction. Nausea tied to fatty meals points here more often than to the stomach.
- Thyroid and adrenal disorders. Both alter motility and appetite. Adrenal insufficiency in particular presents with nausea long before anyone suspects it.
- Cyclic vomiting syndrome. Stereotyped episodes with well periods between them. A family migraine history is common.
- Cannabinoid hyperemesis. Compulsive hot showers are the giveaway. Ondansetron characteristically fails in these cases.
A diagnostic clue hides in how well the medication works. Ondansetron that reliably fails suggests the nausea never travels the serotonin pathway. Attention then shifts toward vestibular causes, raised intracranial pressure or a functional gut-brain disorder. A medication that stops working after months of good response suggests the underlying condition has progressed.
Nutrient status is the piece most often skipped. Chronic nausea suppresses intake, and sustained low intake depletes B12, iron, magnesium and thiamine. Each of those independently worsens nausea and fatigue. The loop closes on itself quickly. Correcting a deficiency sometimes reduces how much antiemetic a person needs.
Keeping a simple record helps more than it sounds. Note what you ate. Note how long after eating the nausea started, and whether vomiting relieved it. Relief on vomiting points toward an obstruction or an emptying problem. No relief points toward a central or metabolic cause. Those two answers narrow the field faster than any single test.
Some patterns call for same-day assessment rather than another tablet. Vomit that looks like coffee grounds or contains blood points to bleeding in the upper tract. Severe abdominal pain with vomiting and no passage of gas suggests obstruction, and a sudden headache with vomiting and visual change belongs in an emergency department that evening.
Timing across the day carries information too. Morning nausea before eating suggests one set of causes, while nausea that builds hours after a meal suggests quite another. Bringing that pattern to an appointment shortens the diagnostic route considerably.
Medical Disclaimer
This article is for general information and does not replace individual medical advice. Discuss ondansetron with a licensed clinician before starting or changing a dose.